Skip to content

Image result for stethoscope Dr. John Mandrola (physician and medical writer) has once again written thought provoking posts about medicine and the need for people to question tests, procedures, screening, and to look at the harms and benefits. Because YES - all of the above have harms and benefits, even something as "minor" as taking an antibiotic for a week or two (for example, effects on the gut microbes).

Excerpts from his April 20 post at drjohnm.org: Trust and Medical Science

I first addressed the lack of skepticism among my colleagues. I argue that doctors have become a rapturous audience for medical news. We too easily accept flawed evidence. Our embrace of a flawed dissolving coronary stent and a left atrial appendage closure device serve as good examples of misplaced optimism.

In the second section of the essay, I explore the problem with overselling science. Here’s an except: Science does not do itself. Humans—bent on having a successful academic career—do science. This means positive results can become the goal rather than the pursuit of scientific truth.

I spent three paragraphs on evangelism over screening healthy people. It crushes the public trust to say “screening saves lives” when the evidence doesn’t support the claim. This is not a typo. I cite numerous studies that show common screening tests, mammography, PSA tests, colonoscopy, when put to the test of a randomized controlled trial, do not lower overall death rates.

The obfuscation comes when screening advocates tout lower disease-specific death rates. Viz, mammography may (slightly) lower the chance of dying from breast cancer but it has no significant effect on all-cause death. Through a colleague [Dr. B. Mazer] on Twitter, I found a wonderful quote on the folly of trying to reduce your risk of dying from one sort of disease. “If you are a patient contemplating some screening test, and the result of that test or treatment is no measurable reduction in the rate of death at some clinically relevant later point in time, then why have the test or treatment—unless the patient, for some reason, has a desire to die from condition A instead of condition B.”

And excerpts from his commentary on this topic at Medscape: Want More Trust in Medical Science? Embrace Uncertainty and Cut the Hype

I see a lot of overconfidence in medical science. At the bedside, clinicians—myself included—underestimate harms and overestimate benefits of medical intervention. These inaccuracies have many causes. One is a lack of skepticism. It was 10 years into practice before I learned that most of a study's bias comes in its planning, in the questions it asks.

Rarely do I hear a practicing colleague or speaker at a medical meeting cite Dr John Ioannidis's famous 2005 paper "Why most published research findings are false." Ioannidis, a Stanford epidemiologist, argues that small sample sizes, tiny treatment effects, "flexible" study designs (which can transform "negative" into "positive" results), prestudy biases, and conflicts of interest are the root causes of false research findings. Research findings, he argues, may simply be an accurate measure of the prevailing bias.....Richard Horton, the editor of the Lancet, agrees with Ioannidis. In 2015, he wrote that "much of the scientific literature, perhaps half, may simply be untrue." One of the (many) reasons for this crisis, Horton adds, is that "in their quest for telling a compelling story, scientists too often sculpt data to fit their preferred theory of the world." 

Another group of academics that threaten the public trust are screening evangelists. Screening is precarious because it puts doctors close to breaking the golden rule—first, do no harm. Doing things to people-without-complaints and promoting the slogan "screening saves lives" should require clearing the highest bar of evidence. The truth, though, is that the evidence does not support such zealous advocacy.

A systematic review of meta-analyses and randomized clinical trials that studied screening of asymptomatic adults for 19 diseases (39 tests, including mammography) found reductions in disease-specific mortality were uncommon and reductions in all-cause mortality were very rare or nonexistent. Prasad and colleagues explain how screening advocates conflate disease-specific death rates with overall mortality. "Using disease-specific mortality as a proxy for overall mortality," they wrote in the BMJ, "deprives people of information about their chief concern: reducing the risk of dying."

Another good Dr. John Mandrola post: Four Crucial Questions To Ask Your Doctor

An article was just published in a research journal to discuss the fact that humans - in part due to lifestyles which include less dietary fiber (due to eating fewer varieties and amounts of plants) and due to medical practices (such as frequent use of antibiotics) has resulted in gut "bacterial extinctions". In other words, humans (especially those living an urban industrialized Western lifestyle) have fewer gut bacterial species than those living a more traditional lifestyle, and this loss of bacterial species is linked to various diseases. Humans can increase the number of certain bacterial species, but the loss of some bacterial species is forever. 

The researchers discuss that humans have the "lowest level of gut bacterial diversity"  of any hominid and primate. They stated that the shrinking of the variety of microbial species in the human gut (the gut microbiome) began early in human evolution (as humans started eating more meat), but that it has accelerated dramatically within industrialized societies. And that evidence is accumulating that this gut bacterial "depauperation" - the loss of a variety of bacterial species - may predispose humans to a range of diseases.  Some of it is due to evolution (as humans ate more meat), and some to lifestyle changes. A term is used throughout this paper: depauperate - which means lacking in numbers or variety of species in the gut microbiome (the microbial community or ecosystem).

Other research has also shown that eating a highly processed Western diet results in gut microbial changes that are linked to various diseases (here, here, here) - that is, the microbes being fed are those associated with diseases. Also, certain diets encourage certain microbial species to flourish (here, here).  Bottom line: studies find health benefits from higher levels of dietary fiber - from fruits, vegetables, seeds, nuts, whole grains, and legumes (beans). From Current Opinion In Microbiology:

The shrinking human gut microbiome

Highlights: Humans harbor the lowest levels of gut bacterial diversity of any hominid. Humans in industrialized nations harbor fewer gut bacterial taxa than any primate. Medical practices and lack of dietary fiber may drive gut bacterial extinctions. Depauperate microbiotas may predispose entire human populations to certain diseases.

Mammals harbor complex assemblages of gut bacteria that are deeply integrated with their hosts’ digestive, immune, and neuroendocrine systems. Recent work has revealed that there has been a substantial loss of gut bacterial diversity from humans since the divergence of humans and chimpanzees. This bacterial depauperation began in humanity’s ancient evolutionary past and has accelerated in recent years with the advent of modern lifestyles. Today, humans living in industrialized societies harbor the lowest levels of gut bacterial diversity of any primate for which metagenomic data are available, a condition that may increase risk of infections, autoimmune disorders, and metabolic syndrome. Some missing gut bacteria may remain within under-sampled human populations, whereas others may be globally extinct and unrecoverable.

A typical human harbors on the order of 1013 bacterial cells in the large intestine. This gut microbiota, which can contain over a thousand species, is deeply integrated with virtually every tissue and organ system in the body. Gut bacteria process difficult to digest components of the diet, promote angiogenesis in the intestine, train the immune system, regulate metabolism, and even influence moods and behaviors.

In contrast to hunter–gatherer to agricultural transitions, adoptions of industrial and post-industrial lifestyles have led to massive reductions in bacterial richness within human gut microbiotas. Individuals living in urban centers in the United States harbor fewer gut bacterial species on average than do individuals living more traditional lifestyles in Malawi , Venezuela, Peru, and Papua New Guinea.....Industrialized and traditional lifestyles differ in many respects, confounding the identification of the specific practices that have led to decreases in gut bacterial diversity within industrialized societies. One potential cause is the rise of food processing and the corresponding reductions in the intake of dietary fiber in favor of simple sugars. Recently, studies in model systems have indicated that long-term reductions in dietary fiber can lead to the extirpation of gut bacterial taxa from host lineages. 

Other potential causes of reduced gut bacterial diversity within industrialized human populations include certain modern medical practices. For example, longitudinal studies in humans have shown that levels of gut bacterial diversity decrease drastically after antibiotic use. Although bacterial richness may recover after treatment is completed, the timeline and extent of the restoration is highly subject-dependent. The consequences of antibiotic use on gut bacterial diversity may be most severe when treatment is administered during the early years of life, before the adult microbiota has fully formed .

This post is more on the theme of nanoparticles and human health. My last post was about a study that examined how inhaled nanoparticles  (for example, from air pollution) travel from the lungs to the bloodstream.

Well, today's post is about a pretty shocking 2016 air pollution nanoparticle study which examined the brains (brain tissue) of 45 dead people  (ages 3 to 92) who had lived for a long time in two places with heavy  particulate air pollution - Mexico City and Manchester, England. Some of the British people also had Alzheimer's disease or dementia.

The researchers found evidence that minute nano-sized particles of magnetite from air pollution can find their way into the brain. There are 2 forms of magnetite (which is an iron ore) - one naturally occurring (jagged edges in appearance), and one found commonly in air pollution (smooth and rounded - from being created in the high temperatures of vehicle engines or braking systems). The researchers are concerned that the air pollution nanoparticles may increase the risk for brain diseases such as Alzheimer's.

One of the researchers (Prof Barbara Maher) has previously identified magnetite particles in samples of air gathered beside a busy road in Lancaster, England and outside a power station. She suspected that similar particles may be found in the brain samples, and that is what happened. "It's dreadfully shocking. When you study the tissue you see the particles distributed between the cells and when you do a magnetic extraction there are millions of particles, millions in a single gram of brain tissue - that's a million opportunities to do damage."..."It's a whole new area to investigate to understand if these magnetite particles are causing or accelerating neurodegenerative disease."

However, it must be stressed that at this time there is no proven link between these magnetite particles and any neurodegenerative diseases. They're just wondering.... they call finding these pollution nanoparticles "suggestive observations".

From Medical Xpress: Toxic air pollution nanoparticles discovered in the human brain

Tiny magnetic particles from air pollution have for the first time been discovered to be lodged in human brains – and researchers think they could be a possible cause of Alzheimer's disease. Researchers at Lancaster University found abundant magnetite nanoparticles in the brain tissue from 37 individuals aged three to 92-years-old who lived in Mexico City and Manchester. This strongly magnetic mineral is toxic and has been implicated in the production of reactive oxygen species (free radicals) in the human brain, which are associated with neurodegenerative diseases including Alzheimer's disease.

Professor Barbara Maher, from Lancaster Environment Centre, and colleagues (from Oxford, Glasgow, Manchester and Mexico City) used spectroscopic analysis to identify the particles as magnetite. Unlike angular magnetite particles that are believed to form naturally within the brain, most of the observed particles were spherical, with diameters up to 150 nm, some with fused surfaces, all characteristic of high-temperature formation – such as from vehicle (particularly diesel) engines or open fires. The spherical particles are often accompanied by nanoparticles containing other metals, such as platinum, nickel, and cobalt.

Professor Maher said: "The particles we found are strikingly similar to the magnetite nanospheres that are abundant in the airborne pollution found in urban settings, especially next to busy roads, and which are formed by combustion or frictional heating from vehicle engines or brakes."

Other sources of magnetite nanoparticles include open fires and poorly sealed stoves within homes. Particles smaller than 200 nm are small enough to enter the brain directly through the olfactory nerve after breathing air pollution through the nose.....The results have been published in the paper 'Magnetite pollution nanoparticles in the human brain' by the Proceedings of the National Academy of Sciences.

A good discussion of the study in The Scientist: Environmental Magnetite in the Human Brain

Image of magnetite nanoparticles from the exhaust plume of a diesel engine. Credit Maher et al study, 2016.
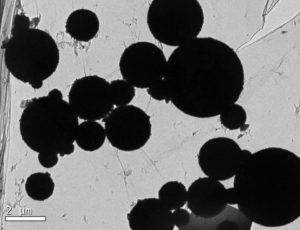


A microscopic image shows magnetite nanoparticles in the human brain. Barbara Maher et al study, 2016.


Image result for earth wikipedia On this Earth Day I want to say: Support science. Support the work of scientists. Science is the pursuit of knowledge. Science is about facts and evidence - not opinions. Medicine is applied science - scientific discoveries are turned into real-world medical treatments. Yes, scientific theories and what we know in science and medicine can change over time as more evidence is found. But science is not political, or it shouldn't be political. This is because we all benefit from science and scientific knowledge.

Sometimes there is bias in science (as when scientists receiving money from a corporation or working for a corporation then do research with results desired by that corporation), but that is why it is important to have transparency in research studies and results, and why good research involves peer review (other scientists review the research) and open discussion, and the importance of others having similar research results in an area. This is also why government funding of basic research is important.

Science is a process of understanding how the world works - it is curiosity driven and uses empirical evidence, particularly information acquired by observation and experimentation. Data is recorded and analyzed by scientists and is part of the scientific method. Basic science results in discoveries that may lead to incredible uses down the road and to amazing benefits to society. An example is the discovery of penicillin, which eventually changed medicine. Government funding has supported basic science for years - for example, NASA, National Oceanic and Atmospheric Administration, National Institutes of Health, and the National Science Foundation. Without government support, most basic scientific research will never happen.

Basically every post I've ever done is science based. Even the ones on sinusitis, Lactobacillus sakei, and the results of self-experimentation. And yes, self-experimentation in science and medicine has a long and honorable history. A very famous example was when the Australian physician Barry Marshall drank a petri dish containing Helicobacter pylori bacteria (from a patient) and soon developed the symptoms of peptic ulcer - this led to his eventually being awarded the Nobel Prize in 2005.

Similarly, through self-experimentation - my four family members, as well as many people writing to me, have reported amazing results within days of using a L. sakei product without changing anything else in their lives. These self-experiments were based on scientific evidence presented in the original Abreu et al study (2012) on sinusitis and the sinus microbiome. This is science at its most basic: doing "A" to a person with condition "B" and seeing the result "C" (which can be a positive effect, no effect, or negative effect).

So take a moment and appreciate all the different fields of science and how they have changed our lives: oceanography, chemistry, physics, earth science, ecology, geology, meteorology, astronomy, zoology, human biology (includes microbiology, anatomy, neurology, immunology, genetics, physiology, pathology, and ophthalmology), botany, anthropology, archaeology, criminology, psychology, sociology, computer science, statistics, mathematics, etc. Some areas of applied science are: engineering, computer science, and medicine. Wow....So please...Support science and the pursuit of knowledge. It's not political. It's not opinions or wishful thinking. Don't deny science.

I think everyone needs to laugh at the silly side of life sometimes. With that said, I am offering the following (all from The New Yorker archives) about health and food:


"Throw out the hummus - from now on, we only eat food too fake to host bacteria."


"Be honest - how much are you exercising?"


Credit: R. Glasbergen

Sooo.....what is going on here? Why are very early onset (5 years and younger) pediatric inflammatory bowel diseases (IBD) in children increasing so rapidly in Canada? Inflammatory bowel diseases include Crohn's disease and ulcerative colitis. In the last two decades there has been an increase of 7.2% per year- to the point that it is among the highest in the world (9.68 per 100,000 children). Only Norway has a similar incidence (10.6 per 100,000 children under the age of 16 years), with Sweden having an incidence  of 12.8 per 100,000. Research studies find that the microbial communities are out of whack (dysbiosis) in IBD.

But why is the rate of IBD increasing in these northern countries? The researchers mention that rates are also increasing in the northern states in the US. Currently the reasons for the higher rates in Canadian and northern European children are not known. Some environmental factors such as lack of sunlight exposure and high rates of vitamin D deficiency, antibiotic use, and diet have been hypothesized as contributing to the pediatric IBD increase. Stay tuned... From Science Daily:

Inflammatory bowel diseases on the rise in very young Canadian children

Canada has amongst the highest rates of pediatric inflammatory bowel disease (IBD) in the world, and the number of children under five years old being diagnosed increased by 7.2 per cent every year between 1999 to 2010, according to a new study by researchers at the Institute for Clinical Evaluative Sciences (ICES), Children's Hospital of Eastern Ontario (CHEO) Research Institute and the Canadian Gastro-Intestinal Epidemiology Consortium.

"The number of children under five being diagnosed with IBD is alarming because it was almost unheard of 20 years ago, and it is now much more common," says Dr. Eric Benchimol, lead author of the study, scientist at ICES and a pediatric gastroenterologist at the Children's Hospital of Eastern Ontario Inflammatory Bowel Disease Centre, in Ottawa. IBD primarily includes Crohn's disease and ulcerative colitis, which are lifelong conditions that cause inflammation in the digestive tract, leading to chronic diarrhea, blood in the stool, abdominal pains and weight loss.

Researchers say a change in the bacterial composition of the gut may be to blame for the increase in IBD cases but they don't know what is causing the change. They suspect a combination of environmental risk factors could be to blame, such as early life exposure to antibiotics, diet, or lower levels of Vitamin D in Canadians.

The researchers found that the incidence of IBD has stabilized in children over the age of five, but in children under five it continues to rise rapidly. The researchers estimate that approximately 600 to 650 children are diagnosed with IBD every year in Canada. [Original study.]

Image result for pills wikipedia Huh?...A recent study found that short-term use (less than 30 days) of commonly prescribed corticosteroid medications are linked to some nasty side-effects: an increase in rates of sepsis,  venous thromboembolism, and fractures. The most common reasons for the prescriptions were for upper respiratory tract infections, spinal conditions, bronchitis, and allergies. The study looked at 1.5 milliion patients, and found that the most common prescriptions written for oral corticosteroids was a six day methylprednisolone “dosepak” (about 47% of prescriptions). Note that while this was an "observational" study (so doesn't prove corticosteroid medication caused the effects), it still is concerning. One should always keep in mind that all medications have side effects, some bigger and some smaller.

Corticosteroids are powerful anti-inflammatory drugs that have been used to treat a variety of diseases for over seven decades. Long term use of corticosteroids is generally avoided because of the risks of serious complications (such as infection, venous thromboembolism, fractures, as well as chronic diseases). However, side-effects of short-term use have been unclear- which is why they are so frequently prescribed (about 1 in 5 Americans or 21% of the people in this study). This is why this study was needed. From Medical Xpress:

Common drugs, uncommon risks? Higher rate of serious problems after short-term steroid use

Millions of times a year, Americans get prescriptions for a week's worth of steroid pills, hoping to ease a backache or quell a nagging cough or allergy symptoms. But a new study suggests that they and their doctors might want to pay a bit more attention to the potential side effects of this medication. People taking the pills were more likely to break a bone, have a potentially dangerous blood clot or suffer a life-threatening bout of sepsis in the months after their treatment, compared with similar adults who didn't use corticosteroids, researchers from the University of Michigan report in a new paper in the British Medical Journal (BMJ).

Though only a small percentage of both groups went to the hospital for these serious health threats, the higher rates seen among people who took steroids for even a few days are cause for caution and even concern, the researchers say. The study used data from 1.5 million non-elderly American adults with private insurance. One in 5 of them filled a short-term prescription for oral corticosteroids such as prednisone sometime in the three-year study period. While the rates of the serious events were highest in the first 30 days after a prescription, they stayed elevated even three months later.

Using anonymous insurance claims data that IHPI purchased for use by U-M health care researchers, they found that half of the people who received oral steroids had gotten them for just six diagnoses, related to back pain, allergies or respiratory tract infections including bronchitis. Nearly half received a six-day prepackaged methylprednisolone "dosepak," which tapers the dose of steroids from highest to lowest. 

Dr. Waljee and his colleagues found higher rates of sepsis, venous thromboembolism (VTE) and fractures among short-term steroid users using multiple different statistical approaches to ensure their findings were as robust as possible....The consistent findings across the three approaches are important given the frequent use of these drugs and potential implications for patients. Waljee notes that the reason for this broad effect of steroids on complications may have its roots in how the drugs work: they mimic hormones produced by the body, to reduce inflammation but this can also induce changes that put patients at additional risk of serious events.

In the meantime, based on the new results, he advises patients and prescribers to use the smallest amount of corticosteroids possible based on the condition being treated. "If there are alternatives to steroids, we should be use those when possible," he says. "Steroids may work faster, but they aren't as risk-free as you might think." [Original study.]

Image result for stethoscope A new Mayo Clinic study reinforces that YES - a person  should get a second opinion when dealing with a complex medical condition. The study compared the referring diagnosis to the final diagnosis of 286 patients referred to the Mayo Clinic by physician assistants, nurse practitioners, and physicians. The researchers found that in only 12 percent of the cases was the diagnosis confirmed. In 21 percent of the cases, the diagnosis was completely changed, while 66 percent of patients received a refined or redefined diagnosis. There were no significant differences between the referring diagnoses made by physician assistants, nurse practitioners, and physicians.

But one concern I have with the study is - how do we know that the Mayo Clinic diagnosis was the correct one, especially in the 21% of cases they gave a completely different diagnosis (what they called "misdiagnosis")? Hmm..? Bottom line: Yes, a second opinion adds to the medical costs, but it may be helpful. From Science Daily:

The value of second opinions demonstrated in study

Many patients come to Mayo Clinic for a second opinion or diagnosis confirmation before treatment for a complex condition. In a new study, Mayo Clinic reports that as many as 88 percent of those patients go home with a new or refined diagnosis -- changing their care plan and potentially their lives. Conversely, only 12 percent receive confirmation that the original diagnosis was complete and correct.

Often, because of the unusual nature of the symptoms or complexity of the condition, the physician will recommend a second opinion. Other times, the patient will ask for one.....To determine the extent of diagnostic error, the researchers examined the records of 286 patients referred from primary care providers to Mayo Clinic's General Internal Medicine Division in Rochester over a two-year period (Jan. 1, 2009, to Dec. 31, 2010). This group of referrals was previously studied for a related topic. It consisted of all patients referred by nurse practitioners and physician assistants, along with an equal number of randomly selected physician referrals.

The team compared the referring diagnosis to the final diagnosis to determine the level of consistency between the two and, thus, the level of diagnostic error. In only 12 percent of the cases was the diagnosis confirmed. In 21 percent of the cases, the diagnosis was completely changed; and 66 percent of patients received a refined or redefined diagnosis. There were no significant differences between provider types.

A possible problem with running marathons is short term kidney injury in the two days right after the race. A study of 22 runners in the 2015 Hartford (Connecticut) Marathon found that most of the runners temporarily developed acute kidney injury (AKI) directly after the race. The study main author Chirag R. Parikh, MD, PhD said: "The kidney responds to the physical stress of marathon running as if it's injured, in a way that's similar to what happens in hospitalized patients when the kidney is affected by medical and surgical complications".

The runners studied fully recovered from the kidney injury 2 days after the event, but the study raises questions about the long-term effects for regular marathon runners, especially in warmer climates. Also, how about the effects of repeated marathons? The researchers say they can only speculate that marathoners adapt to the kidney injury, because they recover within 2 days. But they also pointed out that research has shown there are also changes in heart function associated with marathon running. Something else to keep in mind when considering training for marathons. From Science Daily:

Marathon running may cause short-term kidney injury

According to a new Yale-led study, the physical stress of running a marathon can cause short-term kidney injury. Although kidneys of the examined runners fully recovered within two days post-marathon, the study raises questions concerning potential long-term impacts of this strenuous activity at a time when marathons are increasing in popularity. More than a half million people participated in marathons in the United States in 2015.

While past research has shown that engaging in unusually vigorous activities -- such as mine work, harvesting sugarcane, and military training -- in warm climates can damage the kidneys, little is known about the effects of marathon running on kidney health. A team of researchers led by Professor of Medicine Chirag Parikh, M.D. studied a small group of participants in the 2015 Hartford Marathon. The team collected blood and urine samples before and after the 26.2-mile event. They analyzed a variety of markers of kidney injury, including serum creatinine levels, kidney cells on microscopy, and proteins in urine.

The researchers found that 82% of the runners that were studied showed Stage 1 Acute Kidney Injury (AKI) soon after the race. AKI is a condition in which the kidneys fail to filter waste from the blood. "The kidney responds to the physical stress of marathon running as if it's injured, in a way that's similar to what happens in hospitalized patients when the kidney is affected by medical and surgical complications," said Parikh. The researchers stated that potential causes of the marathon-related kidney damage could be the sustained rise in core body temperature, dehydration, or decreased blood flow to the kidneys that occur during a marathon. [Original study.]

Why is the US Department of Agriculture (USDA) dropping plans to test for glyphosate residues in food? It was supposed to start soon (April 1, 2017), in coordination with the Environmental Protection Agency (EPA) and the Food and Drug Administration (FDA), but now all plans to test have been dropped. Why is this worrisome? The issue is that glyphosate is currently the most widely used pesticide in the world. It is a herbicide that is the active ingredient in the herbicide commonly known as Roundup. Global use was 1.65 billion pounds in 2014 , while overall use in the US was 276.4 million pounds in 2014. Glyphosate is a probable human carcinogen and linked to various health effects, and research shows that glyphosate residues are commonly found in foods.

Even though whether glyphosate is a carcinogen is hotly debated by some groups (with Monsanto fiercely fighting against such a label), it shouldn't matter in the decision of whether to test for glyphosate residues in foods. What is going on with our food, and whether and how much glyphosate residues are in food should be monitored. Government agencies (such as USDA) test for other pesticide residues, and they should do the same for glyphosate, especially because it is so widely used.

The FDA did test for a short while last year (2016) and then stopped in the fall, and yes, they found residues in the foods they studied. Government and private testing has already found glyphosate residues in breast milk, soybeans, corn, honey, cereal, wheat flour, oatmeal, soy sauce, beer, and infant formula. It is currently unknown what the glyphosate residues in food that we eat means for human health. Several studies have linked glyphosate to human health ailments, including non-Hodgkin lymphoma and kidney and liver problems. Of special concern is that because glyphosate is so pervasive in the environment, even trace amounts might be harmful due to chronic exposure. Glyphosate is patented by its manufacturer (Monsanto) for its antibacterial properties - thus it can be viewed as an antibiotic. What is it doing to our gut microbes when ingested? Some people (including researchers) are even suggesting that much of "gluten sensitivity" or "gluten intolerance" that people complain of, may actually be sensitivity to glyphosate residues in food. There are many unanswered questions.

So....is this a case of burying the head in the sand? That there are no problems if no one looks for them? The EPA has long known that glyphosate residues are occurring in food because in 2013 the EPA raised "tolerance limits" for human exposure to glyphosate for certain foods, stating with "reasonable certainty that no harm will result" from human exposure to the chemical. This increase in tolerance levels came about from a request from Monsanto (the manufacturer of the glyphosate herbicide Roundup), and even though numerous groups protested the increase, the EPA went along with Monsanto's request. Some tolerances doubled. Pesticide residues are an important issue - because we don't know what chronic exposure to mixtures of low levels of pesticides (which includes glyphosate) in foods does to us. To babies and children, to pregnant women, to the elderly, to all of us.

But remember.... there are very strong industry pressures on the EPA and USDA, with some government officials also having ties to the industry, and so perhaps it's a case of keeping the head firmly in the sand for all sorts of pesticide issues. Maybe the motto is: see no evil...hear no evil....There have been some lawsuits from people claiming harm from the pesticide, as well as push back from scientists and environmental groups. Some influential scientists and physicians came out with a Statement of Concern in 2016 regarding their serious concerns with glyphosate.

The reason that glyphosate tolerance limits needed to be increased in the USA is because Roundup Ready crops are now so extensively planted, and this has resulted in skyrocketing use of glyphosate in the last 20 years. Roundup Ready crops are genetically modified to tolerate repeated glyphosate spraying (against weeds)  during the growing season. However, the crops take up and accumulate  glyphosate, and so glyphosate residues are increasing in crops. Another reason for increased residue of glyphosate in crops is the current practice of applying an herbicide such as Roundup right at the time of harvest to non-GMO crops such as wheat, so that the crop dies at once and dries out (pre-harvest crop dessication), and which is called a "preharvest application" by Monsanto. Glyphosate is now off-patent so many other companies are also using glyphosate in their products throughout the world.

How to lower your daily intake of glyphosate? Eat organic foods as much as possible, including wheat, corn, oats, soybeans. Glyphosate is not allowed to be used in organic food production. The following excerpts are from an article by journalist Carey Gillam, and it is well worth reading the entire article. From The Huffington Post:

USDA Drops Plan to Test for Monsanto Weed Killer in Food

The U.S. Department of Agriculture has quietly dropped a plan to start testing food for residues of glyphosate, the world’s most widely used weed killer and the key ingredient in Monsanto Co.’s branded Roundup herbicides. The agency spent the last year coordinating with the Environmental Protection Agency (EPA) and the Food and Drug Administration (FDA) in preparation to start testing samples of corn syrup for glyphosate residues on April 1, according to internal agency documents obtained through Freedom of Information Act requests. Documents show that at least since January 2016 into January of this year, the glyphosate testing plan was moving forward. But when asked about the plan this week, a USDA spokesman said no glyphosate residue testing would be done at all by USDA this year.

The USDA’s plan called for the collection and testing of 315 samples of corn syrup from around the United States from April through August, according to the documents. Researchers were also supposed to test for the AMPA metabolite, the documents state. AMPA (aminomethylphosphonic acid) is created as glyphosate breaks down. Measuring residues that include those from AMPA is important because AMPA is not a benign byproduct but carries its own set of safety concerns, scientists believe.

The USDA does not routinely test for glyphosate as it does for other pesticides used in food production. But that stance has made the USDA the subject of criticism as controversy over glyphosate safety has mounted in recent years. The discussions of testing this year come as U.S. and European regulators are wrestling with cancer concerns about the chemical, and as Monsanto, which has made billions of dollars from its glyphosate-based herbicides, is being sued by hundreds of people who claim exposures to Roundup caused them or their loved ones to suffer from non-Hodgkin lymphoma. Internal Monsanto documents obtained by plaintiffs’ attorneys in those cases indicate that Monsanto may have manipulated research regulators relied on to garner favorable safety assessments, and last week, Congressman Ted Lieu called for a probe by the Department of Justice into Monsanto’s actions.

Along with the USDA, the Food and Drug Administration also annually tests thousands of food samples for pesticide residues. Both agencies have done so for decades as a means to ensure that traces of weed killers, insecticides, fungicides and other chemicals used in farming do not persist at unsafe levels in food products commonly eaten by American families. If they find residues above the “maximum residue level” (MRL) allowed for that pesticide and that food, the agencies are supposed to inform the EPA, and actions can be taken against the supplier. The EPA is the regulator charged with establishing MRLs, also called “tolerances,” for different types of pesticides in foods, and the agency coordinates with USDA and FDA on the pesticide testing programs.

But despite the fact that glyphosate use has surged in the last 20 years alongside the marketing of glyphosate-tolerant crops, both USDA and FDA have declined to test for glyphosate residues aside from one time in 2011 when the USDA tested 300 soybean samples for glyphosate and AMPA residues. At that time the agency found 271 samples contained glyphosate, but said the levels were under the MRL - low enough not to be worrisome. The Government Accountability Office took both agencies to task in 2014 for the failure to test regularly for glyphosate.

The USDA’s most recent published report on pesticide residues in food found that for 2015 testing, only 15 percent of the 10,187 samples tested were free from any detectable pesticide residues. That’s a marked difference from 2014, when the USDA found that over 41 percent of samples were “clean” or showed no detectable pesticide residues. But the agency said the important point was that most of the samples, over 99 percent, had residues below the EPA’s established tolerances and are at levels that “do not pose risk to consumers’ health and are safe.” Many scientists take issue with using MRLs as a standard associated with safety, arguing they are based on pesticide industry data and rely on flawed analyses. Much more research is needed to understand the impact on human health of chronic dietary exposures to pesticides, many say.